This site is intended for US healthcare professionals

OPTION-VMS and ADELE-AU real-world studies demonstrated improvements in several patient-reported outcome measures of sleep disturbance with fezolinetant
OPTION-VMS real-world, Phase 4 study preliminary results1,2
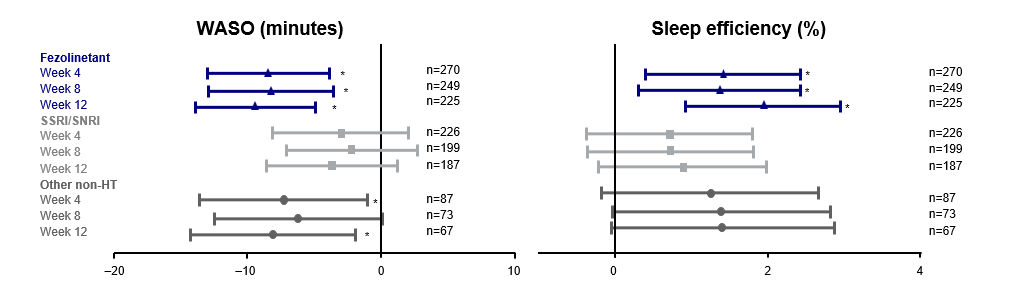
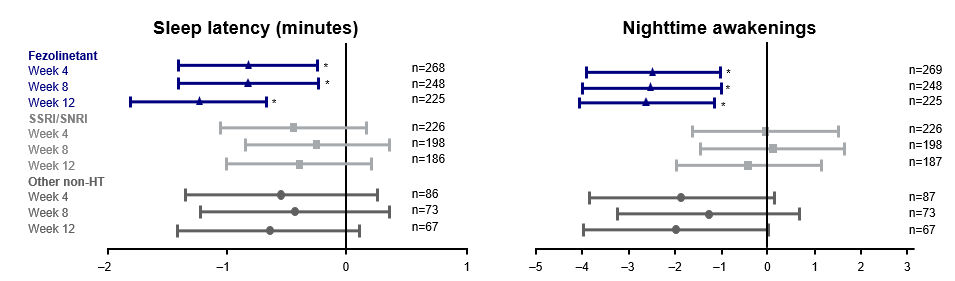
Figure 1. Actigraphy sleep endpoints: adjusted LS mean change (95% CI) from Baseline2
LS: least squares.
*p < 0.05. A bar crossing zero indicates a nonsignificant p-value.
Adapted from: Shapiro M, IMS 2026.
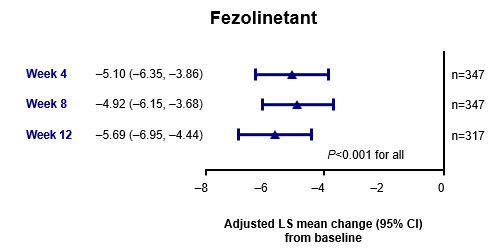
Figure 2. PROMIS SD SF 8b total T-score (fezolinetant treatment): adjusted LS mean change from Baseline2
LS: least squares.
A bar crossing zero indicates a nonsignificant p-value; p < 0.001 for all.
Adapted from: Shapiro M, IMS 2026.
Australian real-world study, ADELE-AU, preliminary results
Figure 3. Women reporting “moderately better” or “much better” improvement in PGI-C SD at Weeks 4, 8, and 12 3
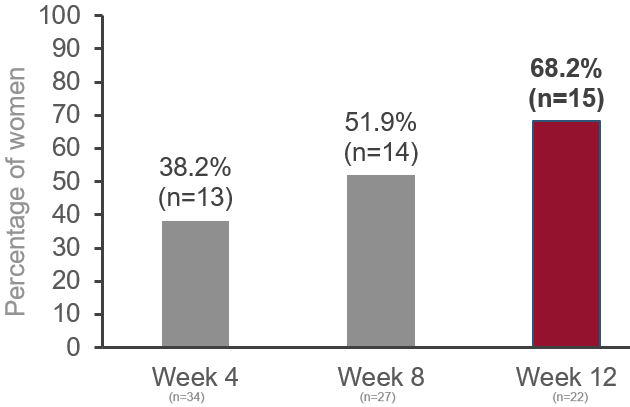
Adapted from: Rodrigo N, Rayment E, Jang C, et al. AMS 2026.
Figure 4. Change in sleep disturbance (PROMIS SD SF 8b) at Weeks 4, 8, and 12 3
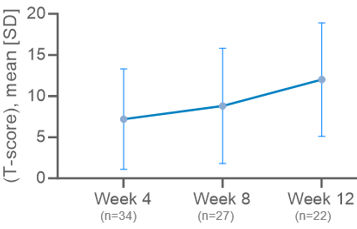
p < 0.001.
Adapted from: Rodrigo N, Rayment E, Jang C, et al. AMS 2026.
Pooled SKYLIGHT 1 and 2 post-hoc analysis4
SKYLIGHT 1 and 2 Phase 3 individual trial results
Figure 5. Change in PROMIS SD SF 8b total score from Baseline to Weeks 4 and 12 in SKYLIGHT 1 and SKYLIGHT 29,10
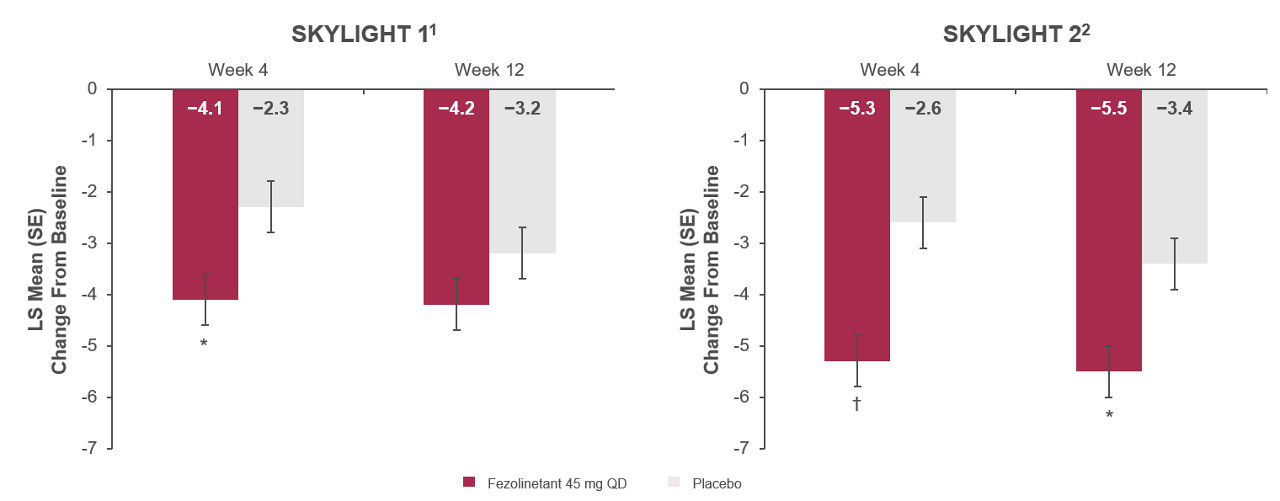
*p<0.01 vs placebo. †p<0.001 vs placebo.
Mean (SD) Baseline values in SKYLIGHT 1: fezolinetant 45 mg, 27.1 (7.0); placebo, 26.4 (6.6).
Mean (SD) Baseline values in SKYLIGHT 2: fezolinetant 45 mg, 26.2 (6.6); placebo 27.4 (7.0).
All randomized participants assessed according to randomization at first dose (SKYLIGHT 1: placebo n = 175, fezolinetant 45 mg n = 174; SKYLIGHT 2: placebo n = 167, fezolinetant 45 mg n = 167).
Adapted from: Lederman S, Lancet 2023 and Johnson KA, J Clin Endocrinol Metab. 2023
Pozlep B. OPTION-VMS: First real-world fezolinetant effectiveness and safety data, including objective sleep data, in a phase 4 observational study of non-hormonal treatments for bothersome menopause-associated vasomotor symptoms [oral slide presentation]. Congress of Slovenian Gynaecologists and Obstetricians (SGC). Ljubljana, Slovenia. 2026.
Shapiro M, Maki PM, Larkin L, et al. Fezolinetant and real-world sleep outcomes in the phase 4 OPTION-VMS study: second preliminary analysis of patient-reported and actigraphy-derived endpoints [oral slide presentation]. International Menopause Society (IMS) 20th World Congress on Menopause. Rio de Janeiro, Brazil. 2026.
Rodrigo N, Rayment E, Jang C, et al. A real-world study describing sleep outcomes among women using fezolinetant in Australia (ADELE-AU): preliminary analysis [oral slide presentation]. Australasian Menopause Society (AMS) Annual Congress 2026. Sydney, AU. 2026.
Cano A, Perry GN, Martins K, et al. Effect of fezolinetant on sleep, health-related quality of life and work productivity. Climacteric. 2026;ahead-of-print(ahead-of-print):1-8. Available at: https://doi.org/10.1080/13697137.2026.2715238.
C.M. MS, Cano A, Nappi RE, et al. Effect of fezolinetant on sleep disturbance and impairment during treatment of vasomotor symptoms due to menopause. Maturitas. 2024;186107999. Available at: https://doi.org/10.1016/j.maturitas.2024.107999.
Thurston RC, Chang Y, Buysse DJ, et al. Hot flashes and awakenings among midlife women. SLEEP. 2019;42(9):zsz131. Available at: https://doi.org/10.1093/sleep/zsz131.
English M, Stoykova B, Slota C, et al. Qualitative study: burden of menopause-associated vasomotor symptoms (VMS) and validation of PROMIS Sleep Disturbance and Sleep-Related Impairment measures for assessment of VMS impact on sleep. J. Patient-Rep. Outcomes. 2021;5(1):37. Available at: https://doi.org/10.1186/s41687-021-00289-y.
DePree B, Shiozawa A, King D, et al. Association of menopausal vasomotor symptom severity with sleep and work impairments: a US survey. Menopause. 2023;30(9):887-897. Available at: https://doi.org/10.1097/gme.0000000000002237.
Lederman S, Ottery FD, Cano A, et al. Fezolinetant for treatment of moderate-to-severe vasomotor symptoms associated with menopause (SKYLIGHT 1): a phase 3 randomised controlled study. Lancet. 2023;401(10382):1091-1102. Available at: https://doi.org/10.1016/s0140-6736(23)00085-5.
Johnson KA, Martin N, Nappi RE, et al. Efficacy and Safety of Fezolinetant in Moderate to Severe Vasomotor Symptoms Associated With Menopause: A Phase 3 RCT. J. Clin. Endocrinol. Metab. 2023;108(8):1981-1997. Available at: https://doi.org/10.1210/clinem/dgad058.
Schaudig K, Wang X, Bouchard C, et al. Efficacy and safety of fezolinetant for moderate-severe vasomotor symptoms associated with menopause in individuals unsuitable for hormone therapy: phase 3b randomised controlled trial. BMJ. 2024;387(387):e079525. Available at: https://doi.org/10.1136/bmj-2024-079525.
The medical information on this website is for educational purposes only and is intended to provide scientific information about Astellas products. This information is not intended as medical advice or clinical recommendations. This website is for use only by United States residents and licensed healthcare professionals (HCPs) practicing in the United States. Product labeling may vary between countries.
Please choose an option that best describes you:
For visitors outside the United States: click here


